Before You Listen
- Prerequisites: basal ganglia direct/indirect pathway anatomy, the dopamine D1/D2 receptor split, the upper motor neuron versus lower motor neuron distinction, and the spasticity-versus-rigidity contrast from REHAB-04.
- Runtime: 1 hour 2 minutes.
- Topic in one line: the hyperkinetic-versus-hypokinetic axis; Parkinson disease (PD) as prototypical hypokinetic disorder with TRAP cardinal features (Tremor, Rigidity, Akinesia/bradykinesia, Postural instability), Hoehn and Yahr staging, and the levodopa-carbidopa backbone; atypical parkinsonian syndromes (progressive supranuclear palsy [PSP], multiple system atrophy [MSA], corticobasal degeneration [CBD], dementia with Lewy bodies [DLB]); deep brain stimulation (DBS) target selection (subthalamic nucleus [STN], globus pallidus internus [GPi], ventral intermediate nucleus [VIM] of thalamus); Lee Silverman Voice Treatment (LSVT) BIG and LOUD; the hyperkinetic differential (essential tremor, Huntington disease, Tourette syndrome, Wilson disease, dystonia, tardive dyskinesia, restless legs syndrome [RLS], drug-induced movement disorders); and the rehabilitation toolkit.
Vignette. A 67-year-old right-handed retired carpenter is referred for a 14-month history of progressive right-hand tremor. He notices the tremor most when his hand rests in his lap during television, and he says it disappears when he reaches for his coffee cup. His wife reports that his face has become “expressionless” and his voice softer. On exam he has a 4-6 Hz pill-rolling resting tremor on the right, cogwheel rigidity at the right wrist, decrementing amplitude on right finger taps, micrographia, and a normal pull test. He has not fallen.
What is the diagnosis, the Hoehn and Yahr stage, the single highest-yield argument against an atypical syndrome, the initial pharmacotherapy, and which two LSVT programs apply?
(Answer at the end of this chapter)
Section 1 — Hypokinetic Spectrum: Parkinson Disease and the Atypical Syndromes
Bottom line: idiopathic Parkinson disease is an alpha-synucleinopathy with progressive substantia nigra pars compacta dopaminergic loss producing TRAP cardinal features, with bradykinesia required for diagnosis, asymmetric onset, and a robust levodopa response; the atypical parkinsonian syndromes are distinguished by red flags (early postural instability, vertical gaze palsy, autonomic failure, alien limb, fluctuating cognition with visual hallucinations) and a weaker levodopa response than idiopathic PD.
Movement disorders divide into two phenotypes: hypokinetic (parkinsonism) and hyperkinetic (tremor, chorea, dystonia, tics, myoclonus). Parkinsonism is a syndrome defined as bradykinesia plus at least one of resting tremor or rigidity. The differential begins with idiopathic PD and expands through the atypical Parkinson-plus syndromes and secondary causes (drug-induced, vascular, normal pressure hydrocephalus, post-encephalitic).
Idiopathic PD is the second most common neurodegenerative disorder after Alzheimer disease, with mean onset around 60 years (young-onset PD before 40 is about 5-10 percent of cases, with slower progression, more dystonia and dyskinesia, and less cognitive involvement) and roughly 1.5:1 male predominance. The cytopathological hallmark is the Lewy body, an intracytoplasmic eosinophilic inclusion of aggregated alpha-synuclein. Lewy bodies spread caudally to rostrally per Braak staging: olfactory bulb and dorsal vagal nucleus, then substantia nigra pars compacta when motor symptoms emerge, then neocortex when cognitive decline develops. By the time motor symptoms appear, 60-80% of striatal dopaminergic terminals are already lost.
Dopamine modulates the basal ganglia through two competing loops. The direct pathway uses D1 receptors to facilitate movement; the indirect pathway uses D2 receptors to suppress it. Dopamine depletion underactivates the direct pathway and overactivates the indirect pathway, producing excess inhibitory output from the GPi to the thalamus.
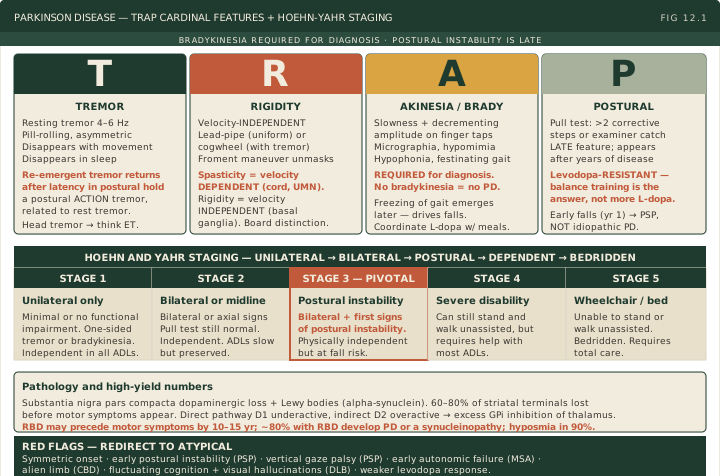
The four cardinal motor features are remembered as TRAP. The tremor is a 4-6 Hz resting tremor with a pill-rolling quality (thumb rhythmically rubs against the index finger), asymmetric at onset, present when the limb is supported against gravity, and diminishes or disappears with voluntary movement and during sleep. A re-emergent tremor reappears after a brief latency in postural hold; it is a postural action tremor of PD, closely related to the rest tremor. Head tremor is rare in PD and should raise suspicion for essential tremor.
Rigidity in PD is velocity-independent resistance to passive movement. This is the critical board distinction: spasticity is velocity-dependent (catch-and-release at high velocity); rigidity is velocity-independent (uniform throughout the range). Lead-pipe rigidity is constant uniform resistance; cogwheel adds the rhythmic catch of the underlying tremor breaking through. The Froment maneuver (voluntary movement of the contralateral limb) augments subtle rigidity.
Bradykinesia is the diagnostic linchpin and is required for diagnosis. It encompasses akinesia (difficulty initiating), bradykinesia proper (slowness), and hypokinesia (reduced amplitude). On rapid alternating finger tapping, the patient shows decrementing speed and amplitude with repetition. Bradykinesia also manifests as micrographia (handwriting that shrinks across the page), hypomimia (masked facies, reduced blink rate), hypophonia (soft monotone voice), shuffling festinating gait with decreased arm swing, en-bloc turning, and a camptocormic forward trunk lean. Freezing of gait (sudden inability to start, turn, or pass through a doorway) is a major cause of falls and emerges later.
Postural instability is the fourth cardinal feature and typically appears late. It is tested with the pull test: the examiner stands behind the patient and pulls backward on the shoulders. An abnormal response is more than two corrective steps backward or requiring the examiner to catch the patient. Postural instability is the most disabling feature because it drives falls, and it does not respond well to levodopa. Prominent postural instability with falls in the first year is the classic red flag for PSP; the current MDS-PSP criteria count repeated unprovoked falls within 3 years of onset.
Hoehn and Yahr staging captures progression. Stage 1: unilateral involvement only, with minimal or no functional impairment. Stage 2: bilateral or midline (axial) involvement without impairment of balance. Stage 3: the pivotal stage; bilateral disease with the first signs of postural instability, still physically independent. Stage 4: severe disability, but the patient can still walk or stand unassisted. Stage 5: wheelchair-bound or bedridden unless aided. The widely used modified scale adds stage 1.5 (unilateral plus axial involvement) and stage 2.5 (mild bilateral disease with recovery on the pull test); the MDS Task Force recommends the original five stages because the half-stages have not been validated. The Unified Parkinson’s Disease Rating Scale (UPDRS) (modern Movement Disorder Society revision: MDS-UPDRS) has four parts: non-motor experiences, motor experiences, motor examination (the most-used in trials, scored on/off medication), and motor complications.
Non-motor features matter. Rapid eye movement sleep behavior disorder (RBD) (acting out dreams due to loss of normal rapid eye movement [REM] muscle paralysis) may precede motor symptoms by 10-15 years; approximately 80% of affected individuals eventually develop PD or a related synucleinopathy. Hyposmia is present in 90%. Constipation is one of the earliest symptoms. Orthostatic hypotension affects 30-58%. Depression affects 35-50%. PD dementia eventually affects 75-90% of long-term survivors. The one-year rule distinguishes PD dementia (dementia beginning more than 1 year after motor disease) from DLB (dementia within 1 year of, or before, motor symptoms); mild cognitive impairment can already be present at PD diagnosis without starting the clock.
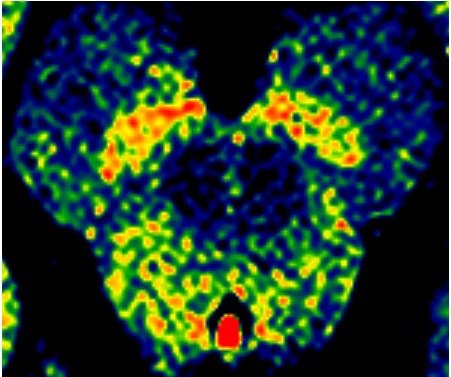
Source: Substantia nigra pars compacta on neuromelanin-enhanced MRI. Gcastellanos, Wikimedia Commons (CC BY-SA 4.0). https://commons.wikimedia.org/wiki/File:Substantia_nigra_pars_compacta.jpg
The atypical parkinsonian syndromes are distinguished by red flags and a weaker levodopa response than idiopathic PD. PSP is a tauopathy with early postural instability and backward falls (classically within the first year; the current criteria count repeated unprovoked falls within 3 years), axial rigidity, vertical supranuclear gaze palsy (downgaze limitation), and pseudobulbar affect. The “hummingbird sign” (midbrain atrophy on midsagittal MRI) supports the diagnosis. MSA is a synucleinopathy with prominent early autonomic failure, cerebellar ataxia (MSA-C), or parkinsonism (MSA-P); MSA-C shows a “hot cross bun” pontine sign. CBD is a tauopathy with markedly asymmetric apraxia, the alien limb phenomenon, cortical sensory loss, and myoclonus. DLB is a synucleinopathy with the triad of fluctuating cognition, recurrent visual hallucinations, and parkinsonism; severe neuroleptic sensitivity (do NOT give haloperidol) is a supporting feature.
Levodopa response is the strongest single supportive feature: idiopathic PD shows a robust, sustained response, and no observable response to high-dose levodopa in moderate disease argues against PD. A good response does not exclude an atypical syndrome: in autopsy-confirmed series about 84 percent of PD, about a third of MSA and 15 percent of PSP responded. Symmetric onset, early autonomic failure, vertical gaze palsy, alien limb, and fluctuating cognition with visual hallucinations all redirect the differential away from idiopathic PD.

Clinical Pearl — Cogwheel rigidity equals tremor superimposed on lead-pipe
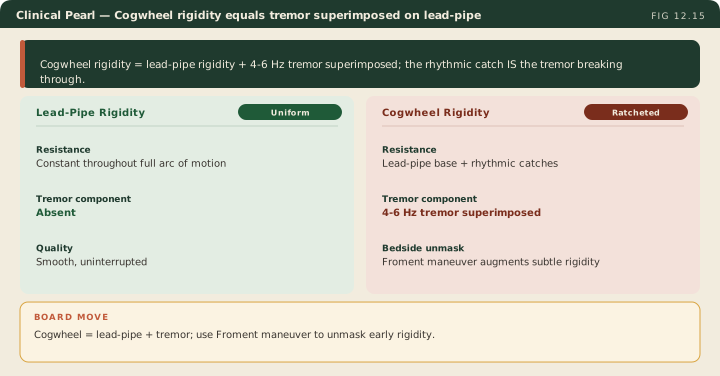
Lead-pipe rigidity is uniform resistance throughout the arc; cogwheel rigidity adds the rhythmic catch of the underlying 4-6 Hz tremor breaking through. The Froment maneuver augments subtle rigidity and is the bedside trick for unmasking early disease.
Board Trap — “Symmetric onset means idiopathic PD”
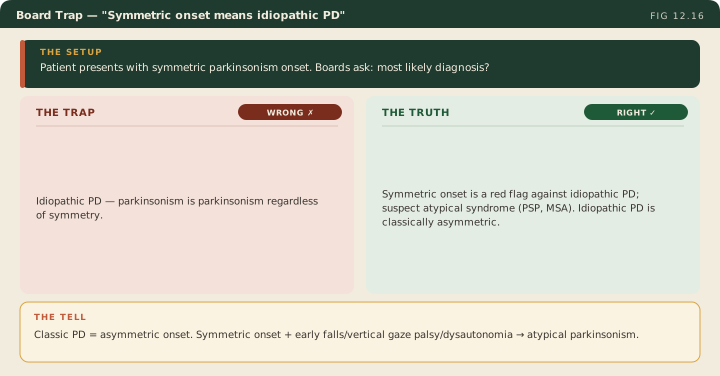
Wrong direction. Idiopathic PD is classically asymmetric at onset, and symmetric presentation is what should raise suspicion for an atypical syndrome (PSP, MSA). Symmetric onset, early postural instability with falls (classically in the first year, within 3 years by current PSP criteria), vertical gaze palsy, dysautonomia preceding parkinsonism, and a weaker levodopa response than idiopathic PD are the red flags that redirect the differential.
High Yield: Hypokinetic essentials

- TRAP: Tremor (resting 4-6 Hz pill-rolling), Rigidity (velocity-INDEPENDENT cogwheel), Akinesia/bradykinesia (REQUIRED for diagnosis), Postural instability (LATE; early falls suggest PSP).
- Pathology: substantia nigra pars compacta dopaminergic loss plus Lewy bodies (alpha-synuclein); 60-80% of striatal terminals lost before symptoms.
- Hoehn and Yahr stage 3 marks the transition to bilateral disease with postural instability.
- Atypical red flags: symmetric onset, early falls (PSP), vertical gaze palsy (PSP), autonomic failure (MSA), alien limb (CBD), visual hallucinations plus fluctuating cognition (DLB).
- One-year rule: dementia within 1 year of motor onset means DLB; dementia more than 1 year after means PD dementia.
- Levodopa response is the strongest single supportive feature for idiopathic PD, but about a third of MSA and 15 percent of PSP also respond, so it never stands alone.
If the cognitive symptoms appear within one year of the onset of motor symptoms, the formal diagnosis is dementia with Lewy bodies. If the cognitive symptoms appear more than one year after the onset of motor symptoms, it is classified as Parkinson’s disease dementia.
— REHAB-12 podcast, ~14:55
By the time that classic resting tremor finally appears in your clinic, 60 to 80 percent of the striatal dopaminergic terminals are already gone.
— REHAB-12 podcast, ~4:58